
Many Capetonians notice shoulder pain that builds through the day and peaks after they lie down. The joint feels fine during morning coffee or a short walk along the Sea Point promenade, yet by midnight the ache makes rolling onto that side impossible.
This pattern is common and rarely random. An experienced shoulder specialist sees it regularly in patients who hike Table Mountain, garden in Constantia, or simply reach for a seatbelt after a long workday.

A common source is irritation or injury of the rotator cuff tendons or the surrounding bursa. Pain at rest and at night, especially when lying on the affected shoulder, is a recognised feature of rotator cuff problems. When the arm rests against the mattress, pressure on already irritated tissue may increase, and without the distraction of daytime movement the pain can feel sharper.
People who spend hours at a desk with rounded shoulders, or who increased outdoor activity once spring weather arrived in October, frequently report a similar pattern. A Cape Town orthopaedic surgeon evaluates the exact structures involved rather than treating the symptom alone.
Leaving the pain unaddressed can carry real costs. Sleep disruption accumulates, and after several weeks of broken nights concentration, mood and recovery from ordinary activity may suffer. Pain can make simple tasks such as lifting a child or loading a cooler for a weekend at Clifton harder.
The NHS notes that shoulder pain can take 6 months or longer to recover, and that stopping use of the shoulder completely can stop it getting better. Stiffness of the joint, often called a frozen shoulder, can last months or years. Getting advice early gives you more options, particularly if you have a big event such as the Nelson Mandela Marathon in mid-October in mind.
A structured approach starts with accurate diagnosis. The shoulder specialist takes a detailed history of activities, previous injuries and night-time positions, then examines the shoulder to see which movements reproduce the pain. Imaging, usually X-rays first and an MRI or ultrasound when soft-tissue detail is needed, helps to show whether the problem is a tendon tear, joint wear or something else. Most people begin with exercises and activity changes guided by a physiotherapist or the orthopaedic team, together with pain relief.
The American Academy of Orthopaedic Surgeons reports that non-surgical treatment relieves pain and improves function in about 80 to 85% of patients with rotator cuff tears. If rest, medication and physiotherapy do not relieve the pain, a steroid injection may help some people, although it does not work for everyone and the length of relief varies. Surgery, including arthroscopic repair, is generally considered when other treatment has not worked or when a person’s circumstances make it sensible. The right plan depends on the diagnosis, which is why assessment comes first.
In Cape Town the same principles apply whether the patient is preparing for the kite festival at Youngsfield or simply wants to sleep through the night before Stormers matches resume. Early assessment by a Cape Town orthopaedic surgeon who regularly treats shoulder conditions keeps options open and shortens the time spent managing escalating symptoms.

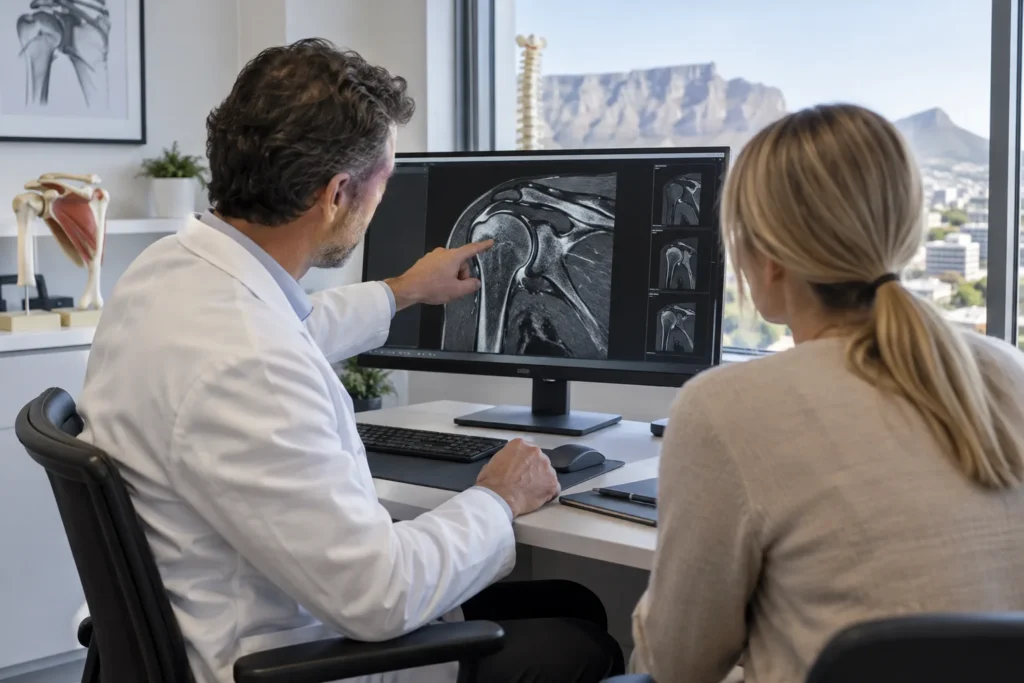
What night-time shoulder pain may be telling you
Night pain is a symptom, not a diagnosis, and more than one problem can cause it. Pain at rest and at night, especially when lying on the affected shoulder, is a recognised feature of rotator cuff tears, according to the American Academy of Orthopaedic Surgeons.
The rotator cuff is the group of tendons that holds the ball of the shoulder in its socket. Other causes of shoulder pain include stiffness of the joint, often called a frozen shoulder, which the NHS describes as a shoulder that is painful and stiff for months and sometimes years. Injury, arthritis and problems with the tendons can all play a part.
Because the possibilities overlap, the pattern of your symptoms is only a starting point. A health professional will examine you to work out the cause and may send you for tests such as an X-ray.
The treatment then depends on the cause. It can include medicine or injections to ease pain and swelling, physiotherapy or exercises to do at home, advice on what to avoid, and sometimes referral to a specialist.
Some features need prompt medical attention. The NHS advises seeking urgent help if the pain is sudden or very bad, if you cannot move your arm, if the arm or shoulder has changed shape or is badly swollen, if you have pins and needles that do not go away or no feeling in the arm, if the shoulder is hot or cold to the touch, if the pain started after an injury such as a fall, if you have severe pain in both shoulders, or if you feel feverish or unwell. These can be signs of something serious, such as a broken or dislocated bone or a torn tendon.
Practical steps while you wait for an assessment
The NHS suggests that most people can do some things to ease shoulder pain themselves. Stay active and gently move the shoulder, because stopping completely can stop it from getting better. Avoid things that seem to make the pain worse, and do not invent strenuous exercises or use heavy gym equipment. When sitting, try to sit upright and rest your arm on a cushion in your lap.
Painkillers such as paracetamol or ibuprofen, and heat or cold packs, can help you keep moving. The NHS describes a pack of frozen peas wrapped in a tea towel, or a hot water bottle wrapped in a tea towel, used for up to 20 minutes at a time. A pharmacist can advise on the best painkiller for you, especially if you have other health conditions.
Because lying on the painful shoulder tends to aggravate it, many people prefer to avoid that position and to use pillows to support the arm. This is a comfort measure rather than a treatment, and what suits one person may not suit another.
Do not use these measures to push through weeks of poor sleep. The NHS advises getting medical help if the pain is getting worse or has not improved after 2 weeks. It also notes that recovery from shoulder pain can take 6 months or longer, so early advice is worthwhile.
What to expect at a first consultation, and how to prepare
A first visit is mostly about understanding your story. You may be asked when the pain began, what you were doing at the time, which positions help or hurt, and how your sleep, work and sport are affected.
The specialist will examine how your shoulder moves and how strong it is. Imaging, such as an X-ray, may be arranged to look for the cause. Further scans are used when the result will change the plan.
It helps to bring a short written timeline, a list of your medication, any earlier scans or reports, and a note of the activities you most want to return to. Useful questions include what the most likely cause is, what the realistic options are in order, how long each option usually takes to show an effect, and what signs should prompt an earlier review.
Treatment is usually staged. Most people begin with exercises and adjusted activity, often guided by a physiotherapist. The American Academy of Orthopaedic Surgeons notes that specific exercises restore movement and strengthen the shoulder, and advises not to attempt shoulder exercises without first consulting a doctor or physical therapist.
If rest, medication and physiotherapy do not relieve the pain, an injection may be considered. A steroid injection helps some people and not others, and the length of relief varies. Surgery is considered when other treatment has not worked or when your circumstances make it sensible, and the decision is shared with you.
Questions people often ask about shoulder pain
Many people ask whether exercise is safe when the shoulder hurts at night. The NHS encourages gentle movement and suggests trying shoulder exercises for 6 to 8 weeks to help stop pain returning, but advice should be matched to your diagnosis.
Others ask whether they can sort out the problem without seeing anyone. Many people manage mild shoulder pain at home, but the NHS says to see a doctor if it is not improving after 2 weeks or if it is very difficult to move the arm. Your doctor can also advise whether physiotherapy would help.
Why early assessment may save time
Waiting and hoping often means weeks of poor sleep and a shoulder that slowly becomes harder to use. An early assessment can rule out serious causes, identify the likely source, and start the right treatment sooner. In many cases the first steps are non-operative, so booking a review does not mean surgery is the plan.
If you live in Cape Town and are unsure where to start, your general practitioner can refer you to a shoulder specialist. This article is general information and not a diagnosis. Any plan should come from a clinician who has examined you.
Frequently Asked Questions
Why does shoulder pain often feel worse at night than during the day?
Pain at rest and at night, especially when lying on the affected shoulder, is a recognised feature of rotator cuff problems. Lying down may increase pressure on irritated tissue, and there is less movement to distract from the pain.
How long should I try home measures before seeing a shoulder specialist?
The NHS advises seeing a doctor if shoulder pain is getting worse or has not improved after 2 weeks, or if it is very difficult to move the arm. Seek urgent help sooner for sudden or very bad pain, if you cannot move your arm, or if the pain followed an injury such as a fall.
Can night pain mean a rotator cuff tear even if I can still move my arm?
It can. Night pain and weakness are recognised features of rotator cuff tears, and a person may still be able to move the arm. Other conditions can cause similar pain, so an examination is needed to find the cause.
Will changing my sleeping position stop the pain?
Lying on the painful shoulder tends to aggravate it, so many people prefer to avoid that position and to support the arm with pillows. This is a comfort measure rather than a treatment, and the cause still needs assessment.
Does a Cape Town orthopaedic surgeon always recommend surgery for night pain?
No. The American Academy of Orthopaedic Surgeons reports that non-surgical treatment relieves pain and improves function in about 80 to 85% of patients with rotator cuff tears. Surgery is generally considered when other treatment has not worked.
Related reading: Why Your Shoulder Pain Gets Worse in Cold, Wet Weather, and When to See a Shoulder Specialist.